Is There a Role for Muscle Relaxants in Migraine Management? A Narrative Review
Article information

Abstract
Migraine is a debilitating neurological condition that affects approximately 15% of the global population and frequently co-occurs with musculoskeletal conditions that add to its burden. Neck pain affects 73%–90% of patients and often prompts off-label prescribing of muscle relaxants to relieve perceived muscular contributions to headache. This narrative review examines the clinical evidence, pharmacological profiles, and safety considerations for centrally acting antispasmodic and antispasticity agents (tizanidine, baclofen, cyclobenzaprine, and methocarbamol), peripherally acting agents (dantrolene), and other agents (carisoprodol and eperisone). Although limited data from landmark trials in the early 2000s suggest potential preventive benefits of tizanidine and baclofen, high-quality, contemporary evidence supporting the routine use of muscle relaxants for migraine is lacking in the broader literature. Their substantial adverse effects, including sedation, dizziness, and the risk of dependence, may further increase patient disability. This review supports current clinical guidelines that prioritize migraine-specific therapies and suggests reserving muscle relaxants for individual cases with prominent musculoskeletal symptoms. Further studies are needed to assess the efficacy and safety of their short- and long-term use in migraine management.
INTRODUCTION
Migraine is a significant neurological condition affecting approximately 15.2% of the global population whilst also accounting for 4.9% of global population ill health (measured in years lost to non-fatal disability), making it one of the leading causes of overall disease burden worldwide.1,2
Recent guidelines issued by the European Headache Federation emphasize that effective migraine treatment should be defined by three main characteristics: headache improvement, non-pain symptom relief and lack of adverse effects.3 This highlights the comprehensive scope that migraine treatment strategies require, implementing evidence-based acute and preventive therapies, while also acknowledging the unmet needs of a patient and factoring in comorbidities alongside any adverse effects. Often, treatment strategies resort to polypharmacy to address the full scope of a migraine attack with all its symptoms.
Although migraine may have varying clinical presentations, musculoskeletal symptoms, particularly neck pain, are frequently associated with migraine and tension-type headache (TTH), with a significant proportion of migraine and TTH patients (73%–90%) also experiencing neck pain.4,5 Gender variations regarding neck pain in migraine patients have also been reported, with one such small-scale cross-sectional study finding that women with migraine have an increased risk of experiencing neck pain and show a higher prevalence of self-reported neck pain.6
The significance of musculoskeletal symptoms including neck pain in migraine raises the question of whether pharmacological interventions aimed at reducing muscular discomfort such as muscle relaxants could provide additional therapeutic benefit in migraine management. Muscle relaxants are a heterogeneous group of medications primarily used in treatment of upper motor neuron disease-related spasticity and muscular spasms or pain as caused by musculoskeletal diseases.7 Despite limited supporting evidence, these medications are occasionally prescribed off label for patients with migraine presenting with musculoskeletal symptoms including neck and shoulder pain as well. From a clinical perspective, muscle relaxants are not considered first-line therapies for migraine and have not been shown to target migraine pathophysiology. In addition, muscle relaxants are not recommended as first-line therapies for migraine prevention or acute treatment according to evidence-based guidelines for the pharmacological treatment of migraine by the International Headache Society.8 Furthermore, there is currently no controlled evidence supporting the use of muscle relaxants for the acute treatment of migraine, and the limited available literature relates primarily to their potential preventive use. Their potential role, if any, is likely limited to a subgroup of patients with prominent musculoskeletal symptoms, such as neck or shoulder pain, where they may serve as adjunctive, symptom-modifying agents rather than disease-specific treatments.
The objective of this narrative review is to review the potential role of pharmacological muscle relaxants in migraine management by reviewing their pharmacological profiles, available clinical evidence, and safety considerations.
METHODS
A literature search was conducted in PubMed using the search terms “muscle relaxants” and “migraine,” combined with the names of individual agents reviewed here (tizanidine, baclofen, cyclobenzaprine, methocarbamol, dantrolene, carisoprodol, and eperisone), from database inception through May 2026. Only English-language publications were considered. Given the narrative design of this review, no formal systematic screening or quality-appraisal process was undertaken. Instead, relevant clinical trials and open-label studies were selectively identified for each agent based on their relevance to migraine management, as determined by the authors.
TYPES AND CLASSES OF MUSCLE RELAXANTS
Muscle relaxants can be broadly categorized into two groups: antispasmodic and antispasticity agents. Centrally acting antispasmodic agents such as cyclobenzaprine and methocarbamol primarily reduce excitatory transmission at spinal and supraspinal levels.9,10 Most common adverse effects of cyclobenzaprine and methocarbamol include dizziness, with methocarbamol also potentially causing headaches and light-headedness.11 The Food and Drug Administration (FDA) has approved cyclobenzaprine for short-term treatment of muscle spasms due to acute musculoskeletal conditions, unrelated to spasticity caused by central nervous system (CNS) disease.11 Methocarbamol is indicated for adjunct use with physical therapy to relieve acute musculoskeletal pain.11
Antispasticity agents such as baclofen and dantrolene have differing mechanisms of action. Baclofen is a chemical structural analogue of the inhibitory neurotransmitter γ-aminobutyric acid (GABA), acting centrally as a selective agonist at the GABA-B receptor, which may modulate central pain processing and muscle tone.12,13 Adverse effects of baclofen include sedation, dizziness, and risks of withdrawal-related delirium with long-term use.14 It is FDA-labeled for use in the treatment of muscle spasms and spasticity as caused by multiple sclerosis and other spinal cord lesions.11 Dantrolene acts peripherally by directly interfering with calcium ion release from sarcoplasmic reticulum in skeletal muscle cells.11 Its adverse effects are significant for CNS depression, fatal hepatotoxicity and dysphagia, and it is indicated for managing spasticity in upper motor neuron disorders including cerebral palsy, multiple sclerosis and spinal cord injuries.11
Tizanidine has both antispasmodic and antispastic activity and is FDA-approved for treatment of spasticity.10,11 It acts centrally through α2-adrenergic agonist activity, without any direct effect on skeletal muscle fibers.11 Adverse effects include drowsiness, dry mouth, somnolence and asthenia, with some groups also reporting vivid dreams and hallucinations.11,15
As of 2026, there are no FDA approvals nor recommendations by major guidelines for use of these muscle relaxants in headache disorders.3
MUSCLE RELAXANTS AND MIGRAINE
Table 1 summarizes the available evidence, proposed mechanisms of action, and limitations for each of the agents discussed below.
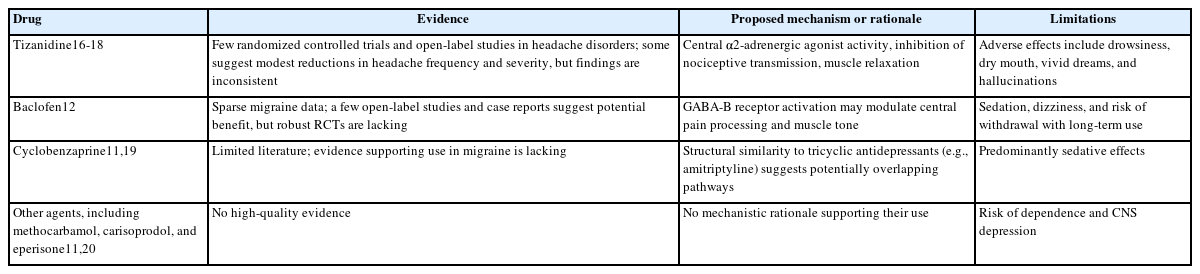
Common muscle relaxants used in migraine: evidence, mechanisms of action, and limitations*
1. Tizanidine
The evidence for use of tizanidine in migraine is limited. Overall, a very small number of randomized controlled trials and open-label studies have investigated tizanidine in primary headache disorders.16,17 Available studies are limited by small sample sizes, methodological heterogeneity, and lack of confirmatory phase III trials.
The clinical validation of tizanidine for headache prophylaxis evolved through a tiered research approach by Saper et al.17 Initial evidence was established in a 2001 open-label dose-titration study, which included 39 patients with more than 15 headache days per month (33 with migraine, five with migrainous headache, one with chronic TTH), and demonstrated that tizanidine was both well-tolerated and potentially efficacious for a broad population with chronic daily headache. However, given the inherent limitations of an uncontrolled pilot, these findings were subsequently rigorously tested in a landmark 2002 multicenter, randomized, double-blind trial, including a larger cohort of 134 patients with chronic migraine, migrainous headache, or TTH. Tizanidine use at a mean dose of 18 mg/day achieved a statistically significant 54.1% improvement in the primary headache index, a clinical measurement calculated as (headache days × average intensity × duration in hours) divided by 28 days compared to only 19.1% in the placebo group.16 Although these studies transitioned tizanidine from a theoretical adjunct to a statistically supported option for managing frequent migraine and TTH cycles, the evidentiary gap caused by lack of recent published data and larger-scale trials remains. Prior studies included heterogeneous populations (e.g., TTH, and migraine), limiting generalizability to migraine-specific populations. In addition, the relatively high doses used may affect tolerability in real-world practice.
It is important to note that there have been recent efforts to expand on Saper et al.’s findings. The TIME trial is a contemporary Phase 3, randomized, double-blind, placebo-controlled study that commenced in 2023 and was designed to re-evaluate the efficacy and safety of tizanidine specifically for the prevention of episodic migraine.18 The study utilizes a 12-week treatment period to measure the change from baseline in the number of monthly migraine days as its primary outcome measure.18 Although this trial represents a critical effort to provide updated, high-quality evidence for the use of tizanidine as an alternative to first-line migraine preventives, it has yet to publish notable results. Given the limited number of randomized controlled trials and the absence of confirmatory contemporary phase III data, tizanidine should not be routinely used for migraine prevention and may only be considered in carefully selected patients with coexisting musculoskeletal symptoms including neck pain.
2. Baclofen
Data on baclofen use in migraine is also sparse. The most significant clinical evidence published comes from a 1999 open-label trial conducted by Hering-Hanit,12 involving a total of 54 patients with migraine, both with and without aura, who were treated with 15–45 mg daily in three doses over 12 weeks. Following a 4-week baseline diary phase and a 12-week treatment period, researchers observed a marked reduction in mean migraine frequency, which declined from 5.48 attacks per month to 1.49 attacks during the final month of the trial, showing efficacy in 86.2% of the 51 patients that completed the study.12 The study also reported that baclofen had shortened the duration and decreased the intensity of attacks.12 These clinical benefits were achieved with a favorable safety profile, as adverse effects were reported as minimal and well-tolerated by the cohort.12 Despite early open-label evidence suggesting potential benefit, baclofen lacks high-quality randomized controlled trial data in migraine populations, and its routine use for migraine cannot be recommended based on available evidence.
3. Cyclobenzaprine
Literature regarding cyclobenzaprine use in migraine is also lacking. Cyclobenzaprine has a structural similarity to tricyclic antidepressants (e.g., amitriptyline), which are effective in migraine prevention, raising questions about whether cyclobenzaprine may share overlapping pathways.11,19 Yet its sedative effect and lack of controlled clinical trials have been limiting its use in migraine.
4. Other agents
These include agents used for their muscle relaxant effects such as methocarbamol, carisoprodol, and eperisone, among others. There are no high-quality clinical studies that evaluate their role in migraine. Concerns include risks of dependency (e.g., carisoprodol), CNS depression, and lack of mechanistic rationale.11,20 The use of these muscle relaxants for migraine cannot be recommended.
PROPOSED MECHANISMS OF ACTION IN MIGRAINE
A key neuroanatomical framework supporting a potential role for muscle relaxants in select patients is the trigeminocervical complex (TCC), where nociceptive afferents from the trigeminal nerve and upper cervical spinal nerves converge.5 This convergence provides a mechanistic basis for the frequent co-occurrence of neck pain and migraine and suggests that peripheral or central modulation of cervical and muscular inputs may influence migraine pain processing in a subset of patients. This synergy suggests that muscle relaxants with central activity may modulate nociceptive signaling within the TCC.21 It must be noted that neck pain in migraine may reflect migraine-related nociceptive processing within the TCC or referred pain rather than a primary musculoskeletal disorder. Therefore, the presence of neck pain alone should not be interpreted as evidence of a muscular treatment target.
Tizanidine exemplifies the convergence of muscle relaxation and pain modulation within the context of migraine prophylaxis. Its proposed mechanism involves the suppression of norepinephrine release and the reinforcement of descending inhibitory pathways, primarily through central α2-adrenoreceptor agonism.16 It has been suggested that tizanidine’s antinociceptive properties are independent of the endogenous opioid system and can be achieved at sub-clinical doses, lower than those typically required to induce skeletal muscle relaxation, offering a nuanced approach to stabilizing hyperexcitable pain pathways.16
Similarly, baclofen also provides a distinct model, as it is thought to exert antinociceptive effects by modulating descending noradrenergic and serotonergic pain pathways, which are key components in the development of migraine pain.12,22 Its ability to bind to GABA-B receptors distinguishes it from other migraine-active agents like valproic acid, which primarily influences GABA-A receptors.12,22
Other agents, such as cyclobenzaprine, methocarbamol, carisoprodol, and eperisone lack migraine pathophysiology-related hypothesis regarding their respective mechanisms of action. Certain antispastic agents may also exhibit secondary sedative, anxiolytic, or antinociceptive properties.10,11
Despite there being some evidence of similar mechanisms, properties and pathways between muscle relaxants and established migraine medications, the exact function of these muscle relaxants has yet to be validated and sufficiently evidenced in the context of migraine. Compared to established migraine preventive therapies, muscle relaxants lack disease-specific mechanisms targeting migraine pathophysiology and are not supported by robust, high-quality evidence. As such, they should not replace guideline-recommended therapies but may be considered only as adjunctive options in carefully selected patients with musculoskeletal comorbidities.
SAFETY CONSIDERATIONS
In addition to commonly reported adverse effects such as sedation and dizziness, muscle relaxants may contribute to cognitive impairment, reduced alertness, and increased fall risk, particularly in older adults, and carry risks of dependence, misuse, or withdrawal syndromes.20,23-25 These effects may be especially problematic in patients with migraine, who frequently experience cognitive symptoms such as “brain fog” during and between attacks. Careful consideration of drug–drug interactions is also warranted, as many patients with migraine are treated with antidepressants, antiepileptics, or other centrally acting agents, increasing the risk of additive CNS depression.
LIMITATIONS
A limitation of this review is that a formal expert consensus process, such as the Delphi method, was not conducted. Therefore, the interpretations presented reflect a narrative synthesis of the available literature rather than a structured consensus among experts. In addition, this narrative review included only English-language publications and focused on commonly used pharmacological muscle relaxants identified by the authors. It did not review other treatment modalities that may be relevant to migraine and associated musculoskeletal symptoms, including medical devices, onabotulinumtoxinA, trigger point injections or physical therapy. Moreover, the available studies primarily evaluated migraine frequency, severity, and duration, with limited assessment of neck pain or other musculoskeletal symptoms as distinct outcomes.
CONCLUSIONS AND PERSPECTIVES
Despite limited evidence for the long-term use of muscle relaxants in chronic pain conditions such as neck pain, current data are too limited to support their routine use in migraine prevention, even though neck pain is a common feature of migraine.15 Moreover, concerns regarding sedation, cognitive side effects, dependency, and drug interactions further constrain their clinical utility, creating a risk–benefit balance that remains essential to consider when prescribing. There is also no evidence supporting their efficacy in reducing migraine burden in patients who have no musculoskeletal symptoms.
Limited information is available regarding the real-world utilization and prescribing patterns of muscle relaxants in migraine, which restricts our understanding of their current role in clinical practice.
Future research should focus on well-designed randomized controlled trials to determine whether subgroups of migraine patients, particularly those with prominent musculoskeletal symptoms such as neck pain, may benefit from targeted muscle relaxant therapy, ensuring adverse events are monitored and considerations for deprescribing if pain related goals are not met. Research is also needed to determine the full scope of gender-related and comorbidity-related variations in treatment response. Moreover, the efficacy of combining muscle relaxants with over-the-counter non-steroidal anti-inflammatory medications or analgesics alongside migraine-specific medications like triptans and gepants should also be explored. From a practical standpoint, the role of muscle relaxants in migraine management remains limited and should be individualized, with careful attention to patient phenotype and risk profile. Moreover, available studies have evaluated muscle relaxants primarily as preventive therapies, and there is currently insufficient evidence to support their use for the acute treatment of migraine. In contrast to established migraine acute therapies such as triptans and non-steroidal anti-inflammatory medications,3 and preventive therapies such as beta-blockers, antidepressants, and newer options like monoclonal antibodies targeting the calcitonin gene-related peptide pathway,26 which are supported by multiple randomized controlled trials and guideline recommendations, the evidence for muscle relaxants remains limited and insufficient to support routine clinical use. Until further definitive data regarding use of muscle relaxants in migraine are available, established evidence-based migraine treatments should be prioritized.26-28
Notes
AVAILABILITY OF DATA AND MATERIAL
Not applicable. All data discussed are derived from previously published, publicly accessible sources cited in the references.
AUTHOR CONTRIBUTIONS
Conceptualization: HB, MWP, CR, ASA; Methodology: HB, JA, KG, MK, MMFP, SA; Writing–original draft: HB, MWP, CR, AS, JA; Writing–review & editing: MK, MMFP, ASA, KG, SA, HB, CR, MWP.
CONFLICT OF INTEREST
Sait Ashina is the International Editor of Headache and Pain Research and was not involved in the review process of this article.
Sait Ashina provided consulting and teaching services for Allergan/Abbvie, Axsome Therapeutics, Eli Lilly and Company, Impel NeuroPharma, Linpharma, Lundbeck, Satsuma, Percept, Pfizer, Teva, and Theranica.
Mario M. F. Peres has received personal fees from Ache, Abbvie, Eli Lilly, EMS, Eurofarma, Libbs, Lundbeck, Novartis, Pfizer, Sanofi, and Teva.
Heba Banihani has received speaking fees from Lundbeck, Pfizer, and Eli Lilly.
Other authors have no disclosures.
FUNDING STATEMENT
None.
ACKNOWLEDGMENTS
None.